- HomeHealthNail Fungus
Fungal nail infections are among the most common foot problems in Britain. So why do the usual treatments leave so many people stuck?
Fungal nail infections turn up in British general practice several times a week. A striking number of patients never finish a treatment course. Dr Liam Thompson, consultant dermatologist, talks through where the standard treatment route tends to fall apart — and what he thinks is actually worth considering instead.

It is one of the most common infections turning up in British consulting rooms — and one of the least likely to be seen all the way through. Dr Liam Thompson is a consultant dermatologist with more than a decade in clinical practice and a long-running professional interest in dermatophyte resistance. In this interview he lays out, in his own words, where the standard treatment pathway for fungal nail infections tends to break down — and what he thinks patients ought to know. The opinions below are his own, drawn from clinical experience, and are not a substitute for your own GP or pharmacist’s advice.

Specialist podiatry appointments are hard to come by, so a lot of people are left trying to manage a fungal nail infection on their own.
Why is toenail fungus a serious health concern in the UK?
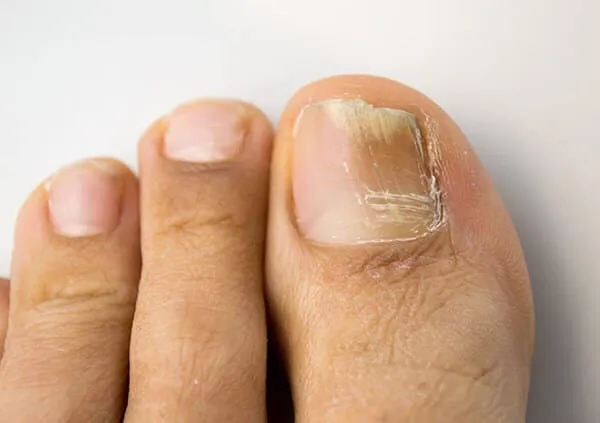
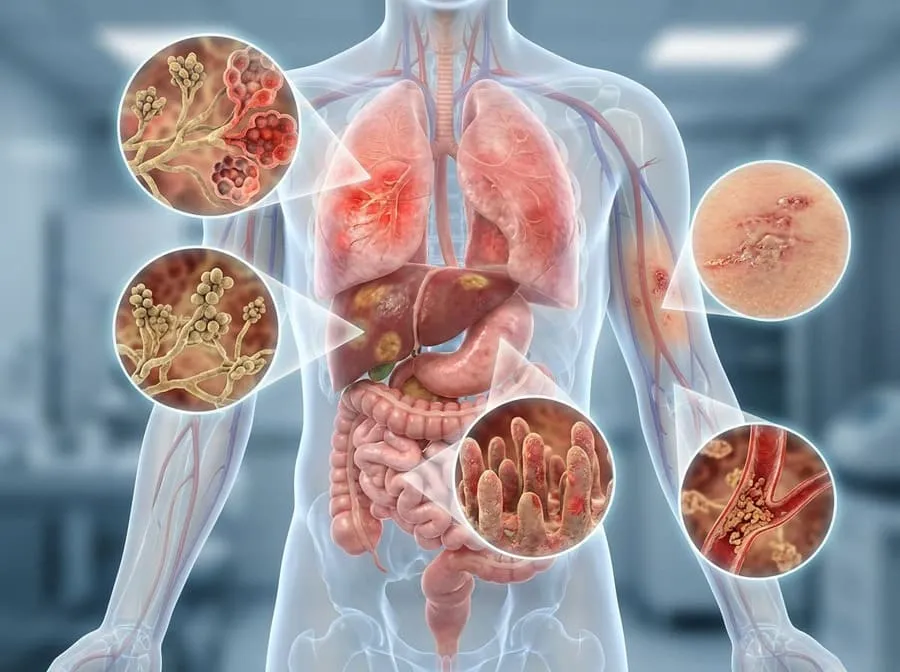
It is a great deal more widespread than most people assume, and the vast majority of cases go unrecorded because the patients never book an appointment about it in the first place. The British maritime climate is more or less perfect for dermatophytes: wellies on the school run holding moisture against the foot, steel-toe work boots on a building site all day, sweaty trainers at the gym, and every leisure centre pool in the country with its shared changing room. The fungus does not stay on the nail either. Left to its own devices it can reach into deeper tissue, and in people with reduced immunity it genuinely needs a GP’s eye on it. Patients who have carried a long-standing fungal infection often describe recurring skin trouble around it too, and a background sense of discomfort they have simply learned to live with.
Which is why, in my own view, onychomycosis deserves rather more attention than it currently gets — from the patient’s side and from the clinician’s.
Why isn’t this condition properly treated?
Partly because patients write it off as a cosmetic problem. By the time they finally book a GP appointment — which, given the access crisis, is already an achievement — the infection has usually had months to spread. The GP has about ten minutes to assess, diagnose and plan. A toenail rarely rises to the top of a long problem list. If terbinafine tablets are prescribed, the patient is now looking at a three- to six-month course with mandatory liver function blood tests and a very real set of side effects. Taste disturbance, nausea and skin rashes are all common enough that a lot of people quietly stop the course early. The over-the-counter alternative, amorolfine nail lacquer — sold in Boots as Curanail or Loceryl for roughly £25 to £30 — needs six to twelve months of weekly application done properly, and most patients tap out well before that. Without consistent follow-through, the fungus just carries on advancing underneath.
Even when the visible yellowing starts to improve, the infection beneath it can carry on indefinitely — and that is where the real downstream problems live.
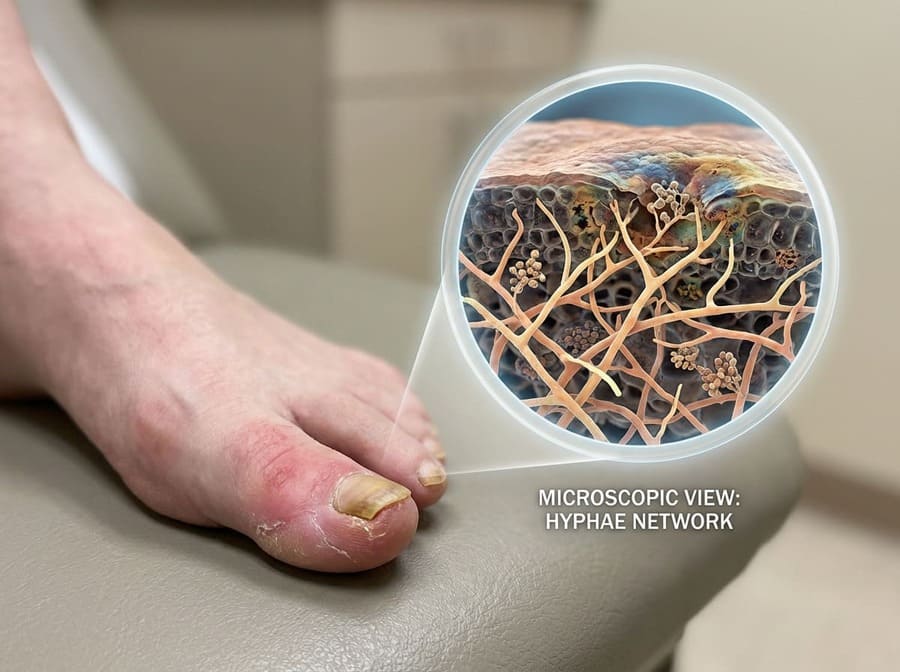
Access is the other half of it. Even where a dermatology referral is on offer, the wait across much of the country is now six to twelve months before a specialist actually sees you. Community podiatry provision has narrowed significantly over the last few years — a lot of services are now prioritising higher-risk patients like diabetics, which leaves everyone else to work it out alone. It varies hugely by postcode. Someone in Surrey might be seen inside a few weeks. Someone in parts of the North East or rural Wales could be waiting the thick end of a year. GPs are stretched thin, running surgeries short-staffed and juggling ten-minute slots against thirty-item problem lists. A fungal nail infection, perceived as low priority, is far too easily filed under ‘cosmetic’ and left to its own devices.
Is this down to doctors being out of their depth?
Not inexperience as such — more a combination of time pressure and limited options. A GP will often tell you to pick up Scholl Fungal Nail Treatment from Boots or Superdrug for about £15, or try Canesten antifungal cream. Those products can help mild athlete’s foot, but they very rarely penetrate a thickened fungal toenail. Curanail (amorolfine 5%) is the strongest nail-specific lacquer available without prescription — but it needs weekly filing and painting for up to a year, and the success rate is only modest even then. Prescribing terbinafine tablets is the most effective systemic option, but it needs baseline liver function tests, carries well-documented side effects, and plenty of patients with pre-existing conditions simply cannot take it. The result is a treatment landscape in which most of the available options manage the appearance rather than resolving the underlying infection.
What should be done? How would you approach this, from the clinic side?
Even the standard treatment guidance acknowledges that creams and lacquers alone are frequently not enough for moderate or severe cases. And yet that is almost always what the patient leaves the room with. What we need in practice is a treatment that reaches both the nail surface and the tissue beneath it — one patients can actually keep doing at home, without the liver monitoring, the blood tests and the side-effect burden of a systemic antifungal. Training more dermatologists and podiatrists would obviously help, but that is a decade-long project at best.
There is, however, something more hopeful. A newer topical option is now available to UK residents directly. In my view it addresses the practical problems with existing over-the-counter options rather better than most of what is currently on the shelf.
The Solution: Orivelle Gel Pen
For the growing group of patients who cannot take terbinafine, who have given up on a lacquer after months of nothing, or who simply cannot get a timely specialist appointment, this plant-based gel pen is a practical alternative. It is designed to tackle fungal activity at the application site, help ease the visible symptoms, and support the skin’s own recovery — without the systemic side effects that come with oral antifungals.
Candidly — I think this could help a great many people around Britain who have essentially been left to sort this out alone. That is why I was pleased to see it brought directly into the UK, rather than waiting years for it to filter through the usual channels.
Who makes this, and why would it work better than the shelf?
The product —Orivelle— was developed by a European dermatological research laboratory and has been reformulated for conditions common in a northern maritime climate. Persistent dampness. Months spent in closed footwear. The condensation that builds up inside wellies and work boots. The gel pen applicator makes daily use genuinely straightforward — a thin layer onto the affected nail and surrounding skin, morning and night. No mess. No filing. No weekly ritual. It absorbs within a minute.
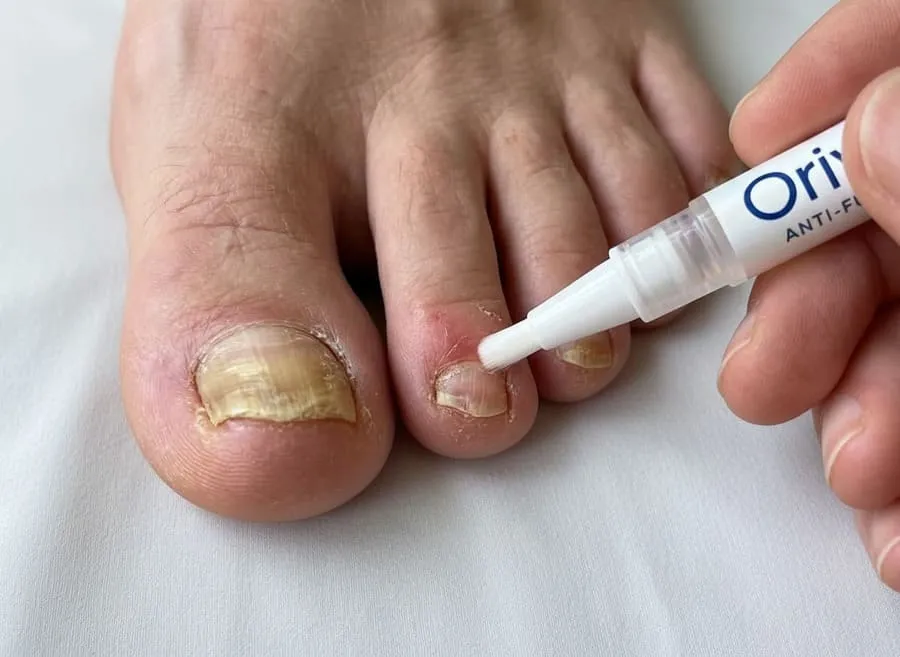
Toenail fungus is stubborn precisely because it lives deep inside the nail — which is why patchy, on-and-off lacquer use nearly always fails. The body’s own immune response is rarely enough to clear an established infection. The Orivelle gel pen format is built to make the twice-daily application that matters actually easy to keep up, while remaining gentle on the surrounding skin.
How users rate Orivelle
Source: self-reported user feedback survey, 2025. Individual experiences vary and this is not clinical evidence of effectiveness.
Orivelleis formulated to help reduce fungal presence at the application site while supporting the skin’s natural barrier. Used consistently, it helps maintain conditions that are less hospitable to dermatophytes. Many users describe a visible difference over a full course, and the pen can be kept in rotation afterwards during higher-risk periods — winter, communal changing rooms. Results vary from person to person.

How does Orivelle compare to Curanail, terbinafine, and Scholl?
Fungi adapt. A lot of what is on the high-street shelf was formulated decades ago, and dermatophyte resistance comes up increasingly often in dermatology practice. The Orivelle gel pen format allows consistent, precise delivery to both the nail surface and the surrounding skin — which happen to be the two sites where reinfection most commonly starts.
In my view it works best as a practical addition to a daily antifungal care routine — particularly for patients the usual treatment pathways haven’t served well.
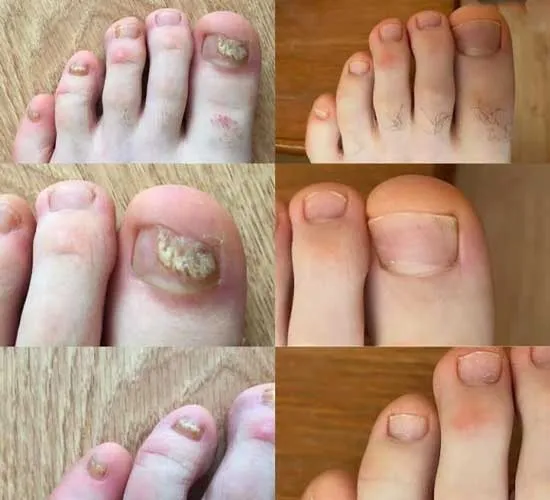
Orivelle treatment timeline: what to expect
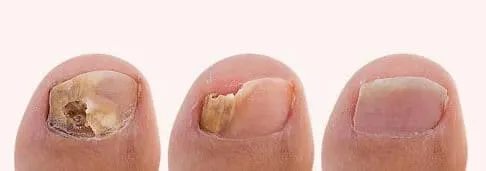
What British users say about Orivelle
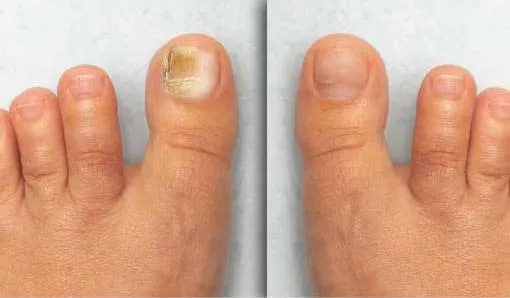 Anna, 50, Guildford, Surrey:“I spent nearly thirty pounds on Curanail from Boots and painted it on religiously every week for five months — barely any difference. My GP referred me to podiatry but said it would be a six-month wait at a minimum. I started on Orivelle while I was waiting, and within a month I could see a real change in the nail. By the time the appointment letter arrived, I honestly didn’t feel I needed it.”
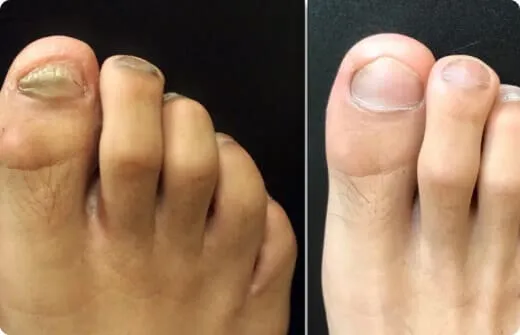 Lily, 46, Chorlton, Manchester:“My GP prescribed terbinafine tablets and I was hopeful, but after six weeks I’d completely lost my sense of taste and was nauseous every morning. The doctor told me to stop the course immediately. I tried Scholl Fungal Nail Treatment from Superdrug next — did nothing. Orivelle is the first thing that has actually made a difference for me, without making me feel dreadful.”
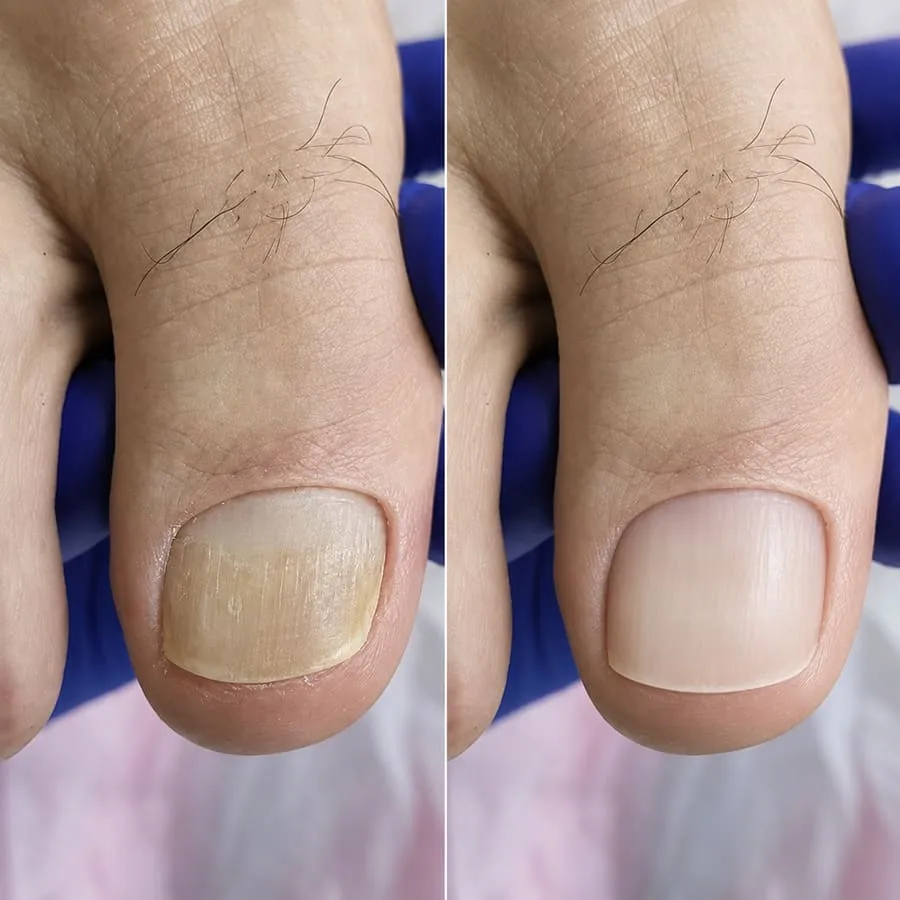 Oscar, 45, Hackney, London:“I picked it up at the Clissold pool — the changing rooms there are always damp. Went to the GP and was told to just get some Canesten cream. It cleared the skin between my toes but the nail itself only got worse. A mate recommended Orivelle, and within three months the nail had grown back looking clear — and it has stayed that way since.”
How can I order Orivelle?
You must be a UK resident and 18 or over.Orivelleships direct from the UK warehouse via Royal Mail or DPD — typically 2 to 4 working days.
Ordering is simple. Answer three quick questions below to unlock your discount, then click “Order now” to secure your course on the officialOrivellesite. You confirm delivery on the next page — no card details are needed to claim the offer.
