If You've Got a Thickened, Yellowing Toenail, Do This Tonight — Before You Spend Another Penny at the Chemist
Updated 4 September 2026 · 7 min read
Here is exactly what I tell every patient who walks in with one of these. Do ittonight. The order matters more than the product does.
First— wash the foot properly and dry it. Nail edge and between the toes included. Most people skip that part and it undoes everything that comes after it.
Then — under a decent light, look at the nail before you put anything on it.One thing decides whether anything you buy has a chance of working.
If the discolouration starts at thefree edge— the tip you'd cut — and creeps back towards the cuticle, and the nail is thickening rather than just staining, then the infection is sittingunderneaththe plate. Not on top of it.
I've been in practice twenty-two years. That one distinction is the thing almost nobody is told, and it is the reason an awful lot of money gets spent for nothing.

I can usually tell before the sock comes off. People come in having not worn a sandal in four summers, and a fair number of them apologise to me — which tells you most of what this condition actually is. It is very rarely about the nail.
I want to be straight about why I'm writing this, because it isn't the article I expected to write.
Nobody is coming to treat this for you — and that changed recently
Here is the bit patients find hardest to believe when I say it out loud.Fungal nails are not routinely treated in community podiatry.The service classes them as a cosmetic problem, which means in most areas it can offer self-management advice and very little else. That isn't a dig at the people doing the work — it is simply how the service is set up, and they have no say in it either.

And the waits behind those doors have got longer, not shorter. Community waiting times are now routinely quoted atover 18 weeks— 18 weeks being the referral-to-treatment standard — with published commentary through 2026 describing sustained demand and workforce pressure across podiatry. So even the patients whodoqualify are waiting the best part of five months.
Which leaves the great majority of people with a fungal nail standing exactly where my patients arrive from — in front of a chemist's shelf, choosing between boxes, with nobody to ask.
The commonest thing I see is not a bad product. It is six years of good money spent on treatments that were never physically able to reach the problem.
Why the shelf keeps failing — and it isn't about strength
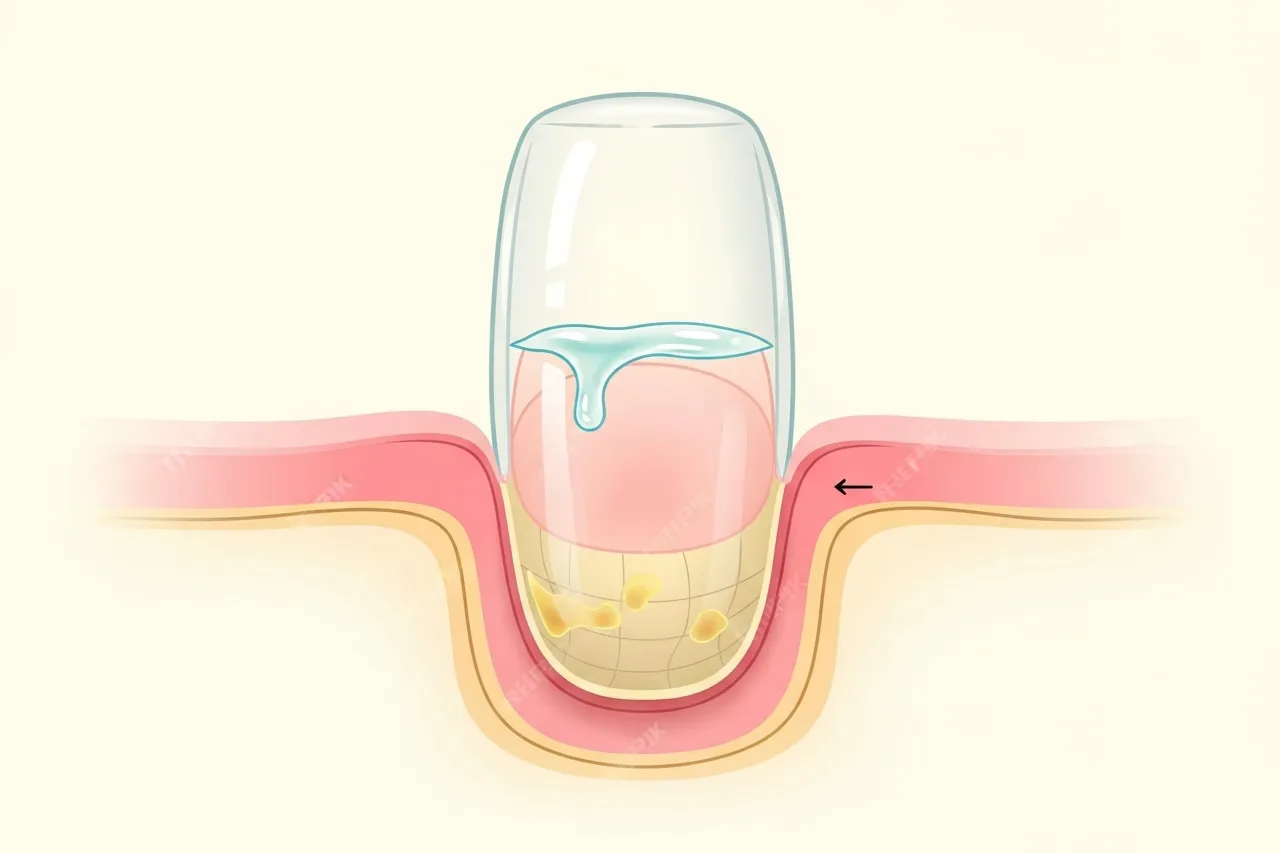
The infection doesn't sit on top of the nail where you can paint over it. It livesunderneath— in the nail bed and inside the layers of the nail plate itself.
The nail iskeratin. Dense, tough, nearly waterproof. It is built by nature to keep things out, and it does the job extremely well — including against whatever you've just paid £28 for.
So the honest answer to "why didn't the lacquer work?" is usually not that it was too weak. It is that the active ingredient mostly justsat there. This is also why clinicians reach for the oral route when they can: the drug arrives at the nail bed from the blood supply underneath, rather than trying to cross the plate from above. In the published literature the standard oral course clears the fungus itself in around76%of patients (mycological cure) — but it's a months-long prescription course with blood monitoring, and for a cosmetic-classed nail most people are never offered it.
What I tell patients to look for instead is not astrongerbottle. It's one built aroundgetting in— small-molecule carrier oils that can actually travel through the keratin layers and take the actives with them, rather than sitting on the surface hoping.
What I started recommending — and why I resisted it for a year
I'll be honest, I was slow to it. Patients kept mentioning the same thing — theOrivelle Nail Care Pen— and my first instinct was the eye-roll I give most things that arrive by word of mouth.
Two things changed my mind. The first is that it isn't a single ingredient. It is a blend of14 botanical oilsdoingdifferent jobs— some are small-molecule carriers chosen to get through the keratin, some go at the fungus itself, and some condition the wrecked nail bed underneath. After twenty-two years of watching single-active lacquers fail against the same bit of physics, that was the first thing I'd read that actually addressed the obstacle.
That was the question I had, and it was the only reason I stopped dismissing it: jojoba and camellia are small enough to move through the plate and drag the actives with them. That is a different problem being solved — not a stronger version of the same one.
The second thing is what started happening in my own treatment room. Patients I'd given the usual self-management talk to came back at six and eight weeks with a band of clear nail at the base. Not all of them. But enough of them that I stopped dismissing it.
What's actually in the pen
The 14 botanicals grouped by what each one does:

The routine I give patients — and why it starts tonight
I saytonightfor a specific reason, not for urgency. The nail is at its most receptive when it is clean, completely dry, and about to spend eight hours inside a dry sock rather than a shoe. Applied in the morning, half of what you put on is gone before lunch.

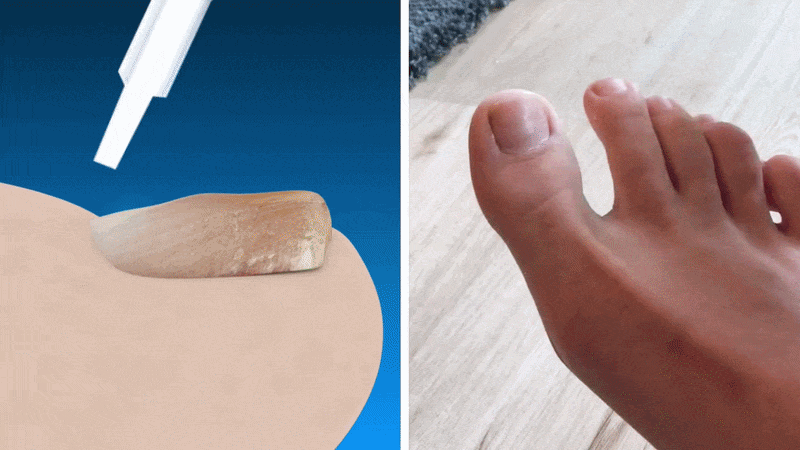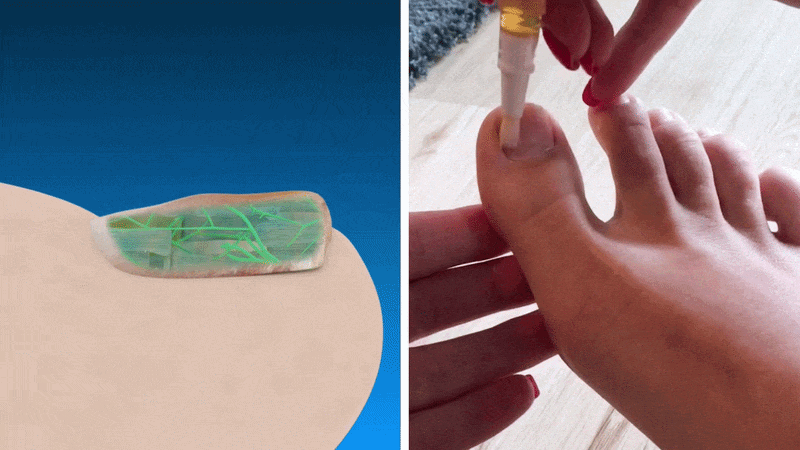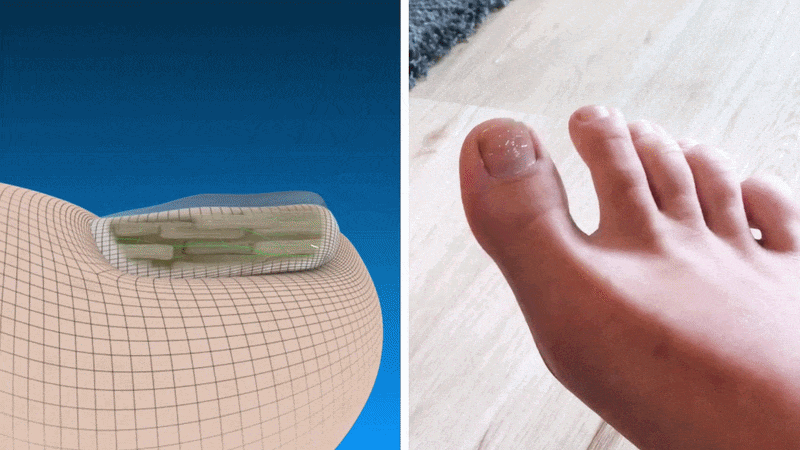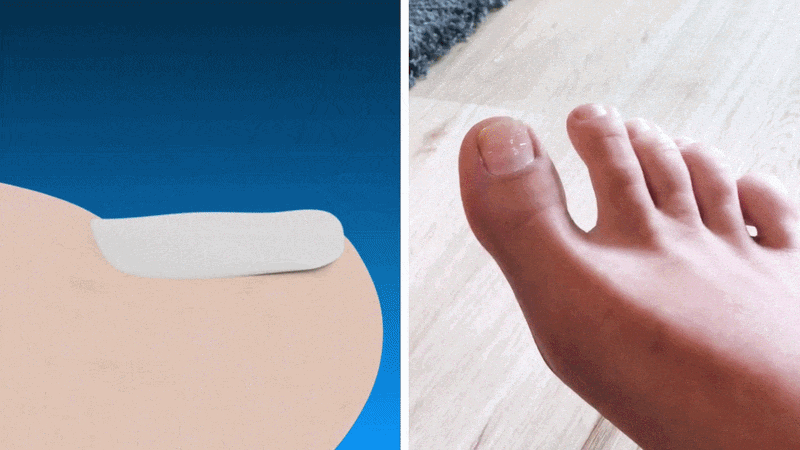
Twice a day is better than once if you will actually keep it up. But the night application is the one that matters — if you only manage one, make it that one.
What to realistically expect, week by week
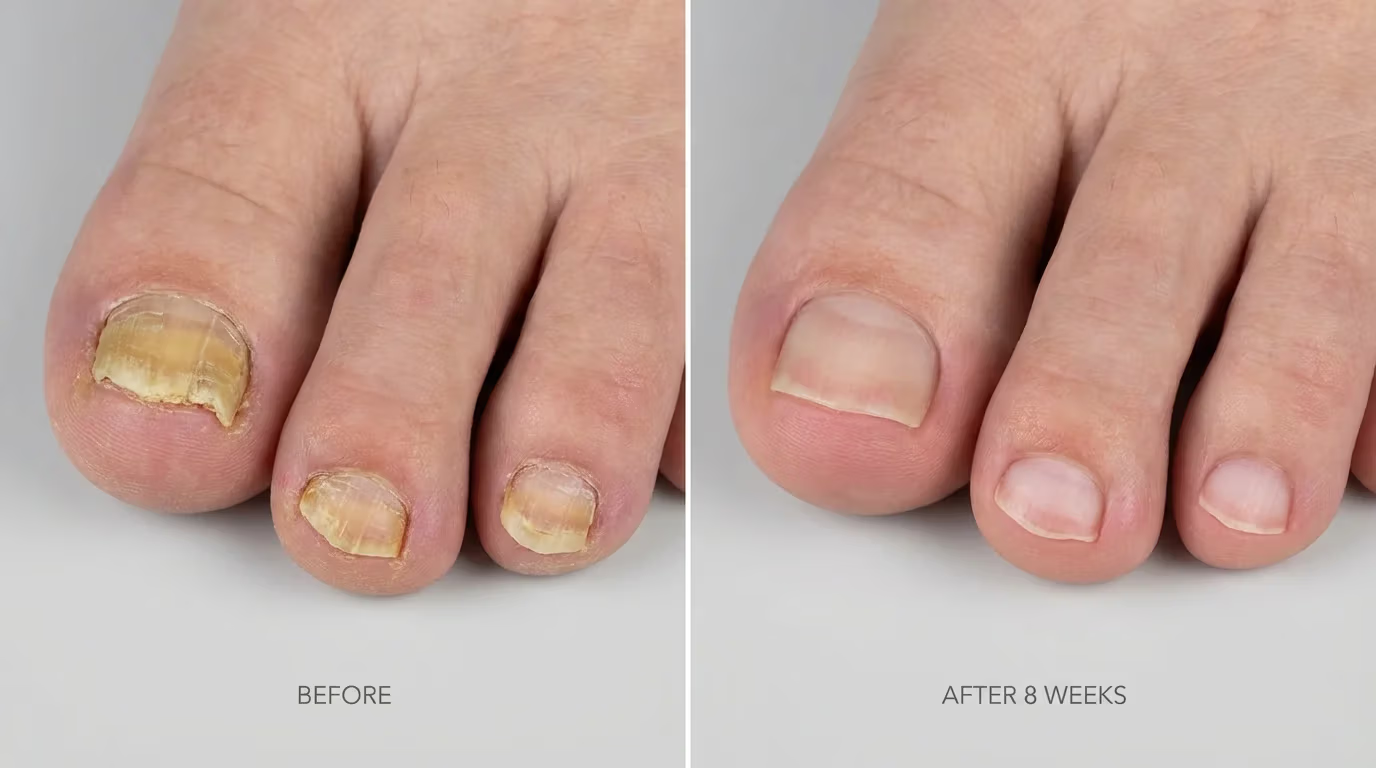
I'm going to be careful here, because this is the point at which most advertising starts lying to patients and I'd rather keep my reputation. Nails grow slowly. Results vary. Some infections do not respond to anything topical at all.
And if there is no clear band at the base by week six, that is useful information too — it means this is one for a doctor, not a shelf.
See the Orivelle Pen & UK Pricing →What patients have told me since
I asked a handful of people who'd been through it whether I could quote them. These are the sorts of thing I hear back, in their own words.
Editor's note. The figures below were supplied by the manufacturer, and availability was checked at the time of writing.
Figures supplied by the manufacturer. Individual results may vary.
See Orivelle & the UK Launch Price →What the alternatives cost — the conversation I have every week
This is the part of the appointment patients find hardest, so I'd rather they read it here first, sitting down, than hear it from me with their shoes off.
What people are quoted vs. what the pen costs
I am not going to pretend the pen does what a laser does. I am saying that for the great majority of people standing in front of that shelf, the realistic choice was never "pen or laser" — it was "pen or another year of the same bottle".
 Get Your Orivelle Pen — Free UK Delivery →
The questions I get asked in the room
"Will it smell like the chemist ones?"— No. You can do it in front of the telly and nobody is any the wiser, which is a bigger factor in whether people finish a course than most clinicians admit.
"How long before I see anything?"— Crumbling often settles inside a fortnight. Visible new nail takes longer, because nails grow slowly and there's no way around that. Judge it at the base at week six, not the tip at week two.
"What if it does nothing for me?"— Then you've learned something worth knowing, and there's a30-day money-back guarantee, so the cost of finding out is a refund and an email. That is a far better deal than the £280 of shelf products I see patients arrive with — none of which came with one.
"Should I still see my doctor?"— Yes. And I mean this seriously. If the nail is painful, if the surrounding skin is red or breaking down, if it's spreading, or if you'rediabetic or have any circulation problem, do not self-treat — see your GP or a podiatrist. A fungal nail on a diabetic foot is not a cosmetic issue and should never be managed off a shelf.
If you take one thing from this: clean, dry, last thing at night — and judge it at the base of the nail at week six.
If you want to try the pen I've been recommending, it's still at the UK launch price.
Claim the Orivelle UK Launch Price →